Drawing based on the label description. No photo yet.
SG 368 pill
Pill with imprint SG 368 is red, round, 8 mm and has been identified as Amlodipine and Olmesartan Medoxomil 10 mg / 40 mg. It is used for high blood pressure. It is supplied by Sciegen Pharmaceuticals, Inc.
Amlodipine and Olmesartan Medoxomil 10 mg / 40 mg
- Imprint
- SG 368
- Strength
- Amlodipine 10 mg / Olmesartan Medoxomil 40 mg
- Used for
- High blood pressure
- Color
- Red
- Shape
- Round
- Size
- 8 mm
- Score
- No score line
- Form
- Tablet, film coated
- Manufacturer
- Sciegen Pharmaceuticals, Inc
- Drug class
- Calcium channel blocker (blood pressure and heart medicine)
- NDC
- 50228-368, 50228-368-30, 50228-368-90, 50228-368-10, 69238-2674, 69238-2674-1, 42291-004, 42291-004-30
Source: the official drug label on DailyMed (US National Library of Medicine). Last checked .
Report a mistake
What is Amlodipine and Olmesartan Medoxomil used for?
Amlodipine and Olmesartan Medoxomil is used for high blood pressure.
- Medicine type
- Calcium channel blocker (blood pressure and heart medicine); ARB (blood pressure medicine)
Official uses from the US prescribing label
Amlodipine and olmesartan medoxomil tablets are indicated for the treatment of hypertension, alone or with other antihypertensive agents, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular (CV) events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including the class to which this drug principally belongs. There are no controlled trials demonstrating risk reduction with amlodipine and olmesartan medoxomil tablets. Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than one drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC). Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly. Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal. Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Amlodipine and olmesartan medoxomil tablets may also be used as initial therapy in patients who are likely to need multiple antihypertensive agents to achieve their blood pressure goals. Patients with moderate or severe hypertension are at relatively high risk for cardiovascular events (such as strokes, heart attacks, and heart failure), kidney failure, and vision problems, so prompt treatment is clinically relevant. The decision to use a combination as initial therapy should be individualized and should be shaped by considerations such as baseline blood pressure, the target goal, and the incremental likelihood of achieving goal with a combination compared to monotherapy. Individual blood pressure goals may vary based upon the patient’s risk. Data from an 8-week, placebo-controlled, parallel-group factorial study provide estimates of the probability of reaching a blood pressure goal with amlodipine and olmesartan medoxomil tablets compared to amlodipine or olmesartan medoxomil monotherapy. The figures below provide estimates of the likelihood of achieving the targeted systolic or diastolic blood pressure goals with amlodipine and olmesartan medoxomil tablets 10 mg/40 mg compared with amlodipine or olmesartan medoxomil monotherapy, based upon baseline systolic or diastolic blood pressure. The curve of each treatment group was estimated by logistic regression modeling from all available data of that treatment group. The right tail of each curve is less reliable because of small numbers of subjects with high baseline blood pressures.
The figures above provide an approximation of the likelihood of reaching a targeted blood pressure goal (e.g., Week 8 SBP <140 mmHg or <130 mmHg or a DBP <90 mmHg or <80 mmHg) for the high-dose treatment groups evaluated in the study. Amlodipine and olmesartan medoxomil tablets 5 mg/20 mg, the lowest dose combination treatment group, increases the probability of reaching blood pressure goal compared with the highest dose monotherapies, amlodipine 10 mg and olmesartan medoxomil 40 mg. For example, a patient with a baseline blood pressure of 160/100 mmHg has about a 48% likelihood of achieving a goal of <140 mmHg (systolic) and a 51% likelihood of achieving a goal of <90 mmHg (diastolic) on monotherapy with olmesartan medoxomil 40 mg, and about a 46% likelihood of achieving a goal of <140 mmHg (systolic) and a 60% likelihood of achieving a goal of <90 mmHg (diastolic) on monotherapy with amlodipine 10 mg. The likelihood of achieving these same goals increases to 63% (systolic) and 71% (diastolic) on amlodipine and olmesartan medoxomil tablets 5 mg/20 mg, and to 68% (systolic) and 85% (diastolic) on amlodipine and olmesartan medoxomil tablets 10 mg/40 mg.
From the FDA-approved label on DailyMed (published Jan 26, 2026).
Doctors sometimes prescribe a medicine for other reasons too. If you are not sure what yours is for, ask your pharmacist.
Is this your pill? Check every detail
- Your pill shows SG 368. The parts can be split between the two sides, so turn the pill over and check both.
- It is red, round, 8 mm.
- Its score line and coating match the details on this page.
- It came from a pharmacy package that names the same drug.
Ingredients
Active: Amlodipine Besylate, Olmesartan Medoxomil
Inactive: Microcrystalline Cellulose, Starch, Corn, Croscarmellose Sodium, Silicon Dioxide, Magnesium Stearate, Polyvinyl Alcohol, Unspecified, Polyethylene Glycol 3350, Polyethylene Glycol 8000, Titanium Dioxide, Talc, Ferric Oxide Yellow, Ferric Oxide Red, Ferrosoferric Oxide
Also distributed by
Amneal Pharmaceuticals Ny LLC, Avkare
Pills that look similar but are different drugs
Same color and shape, different medicine. This is why the imprint matters.
-
 EE
Enalapril Maleate 10 mg
Red, round, 9 mm
Used for severe high blood pressure and heart failure
-
 AN 54
Demeclocycline 150 mg
Red, round, 9 mm
Used for urinary tract infections (UTIs) and gonorrhea
-
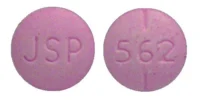 JSP 562
Levothyroxine Sodium 112 mcg
Red, round, 7 mm
Used for goiter and myxedema
-
 9 3 7207
Mirtazapine 30 mg
Red, round, 9 mm
Used for depression
-
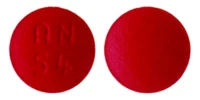 AN 54
Demeclocycline Hydrochloride 150 mg
Red, round, 9 mm
Used for urinary tract infections (UTIs) and gonorrhea
-
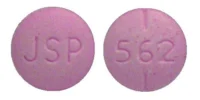 JSP 562
Levothyroxine Sodium 0.112 mg
Red, round, 7 mm
Used for goiter and myxedema
Other Amlodipine and Olmesartan Medoxomil pills
- OA2 Amlodipine Besylate and Olmesartan Medoxomil 10 mg / 20 mg Orange, round, 8 mm Used for high blood pressure
- C74 Amlodipine Besylate and Olmesartan Medoxomil 10 mg / 20 mg Orange, round, 8 mm Used for high blood pressure
- 567 G Amlodipine and Olmesartan Medoxomil 10 mg / 20 mg Orange, round, 8 mm Used for high blood pressure
- K 29 Amlodipine and Olmesartan Medoxomil 10 mg / 20 mg Orange, round, 8 mm Used for high blood pressure
- SG 367 Amlodipine and Olmesartan Medoxomil 10 mg / 20 mg Orange, round, 7 mm Used for high blood pressure
- 83 I Amlodipine and Olmesartan Medoxomil 10 mg / 20 mg Orange, round, 8 mm Used for high blood pressure
- H A10 Amlodipine and Olmesartan Medoxomil 10 mg / 20 mg Orange, round, 9 mm Used for high blood pressure
- A24 Amlodipine and Olmesartan Medoxomil 10 mg / 20 mg Orange, round, 8 mm Used for high blood pressure